 Monitor Simulator
ECG rhythm library
These are the 22 rhythms the simulator can put on the monitor, printed on standard ECG paper at 25 mm/s and 10 mm/mV. Each strip was drawn by the same engine that runs the live monitor, so this is exactly what your learners will see. To test yourself, try the 15 practice strips with answers.
Normal
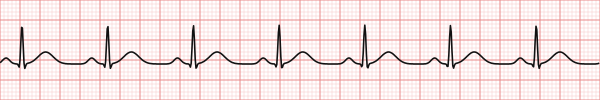
Sinus rhythm
A P wave before every QRS, a constant PR interval and a regular rate between 60 and 100. The reference every other strip is read against.
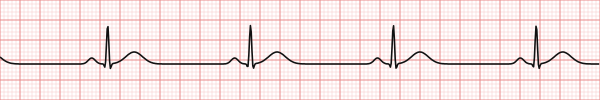
Sinus bradycardia
Normal P waves and conduction, just slow. Shown here at 42. Compare it with the junctional escape rhythm further down, which has a similar rate but no P wave in front of the QRS.
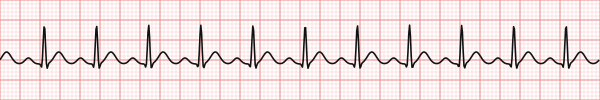
Sinus tachycardia
Every beat still starts with a P wave, but the rate is above 100. The most common rhythm in the scenarios on this site, because it is how pain, fever, bleeding and fear all look on a monitor.
ACS and bundle branch block
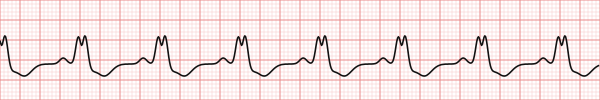
Wide QRS: LBBB or RBBB
A QRS wider than three small squares with a notched shape, and a T wave pointing the opposite way to the QRS. On a single monitor lead you cannot tell left from right, which is why the app treats them as one.
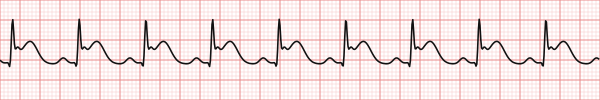
ST elevation
The J point sits above the baseline and the ST segment runs convex upward into the T wave. A monitor lead can raise the suspicion, but a 12-lead ECG makes the diagnosis.
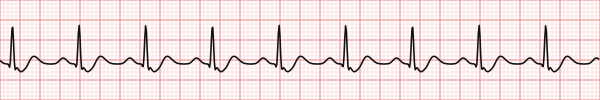
ST depression
A flat or downsloping ST segment below the baseline, here at a rate of 90. Ischaemia, or a reciprocal change elsewhere, and a reason to take a 12-lead.
Arrhythmias
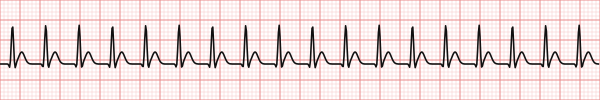
SVT
A narrow, perfectly regular tachycardia around 180 with no visible P waves. The regularity is what separates it from fast atrial fibrillation.
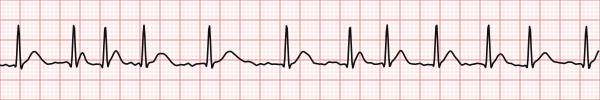
Atrial fibrillation
No P waves and an irregularly irregular R-R interval. On the monitor the short beats also give a smaller pulse on the arterial line and pleth, because the ventricle had less time to fill.
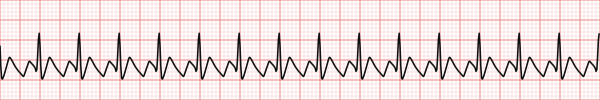
Atrial flutter
Sawtooth flutter waves at twice the ventricular rate, conducted 2:1. A regular rate of exactly 150 should always make you look for flutter.
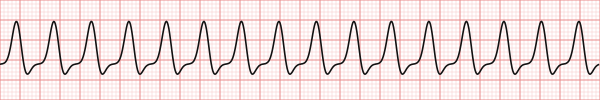
VT with a pulse
Broad, regular complexes at 160. The patient still has a pressure on the monitor, which is what separates this from pulseless VT in the arrest section.
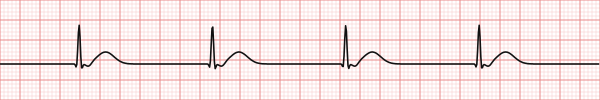
Junctional escape rhythm
Narrow QRS at 40 to 60 with no P wave in front. Look just after the QRS: there is a small inverted P from retrograde conduction.
AV block
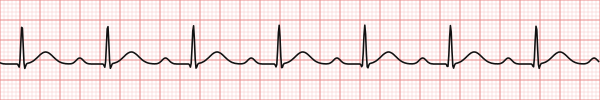
First-degree AV block
Every P wave is conducted, but the PR interval is longer than one large square. The rate is unaffected.
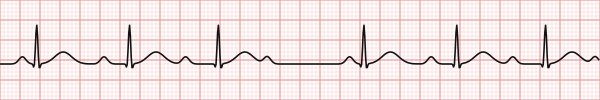
Mobitz type I (Wenckebach)
The PR interval grows beat by beat until a P wave is not followed by a QRS, then the cycle starts again. The grouped beats are the clue from across the room.
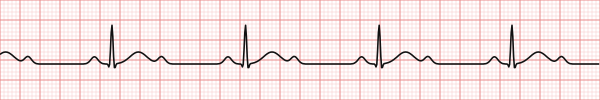
Second-degree AV block, 2:1
Every other P wave is conducted. With a fixed 2:1 ratio you cannot tell Mobitz I from Mobitz II on one lead, so the app shows it as 2:1 and leaves the discussion to the debrief.
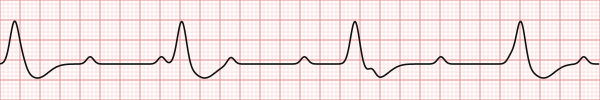
Third-degree (complete) AV block
P waves march through at their own rate while slow ventricular complexes, here at 35, keep a rhythm of their own. The PR interval is different every beat because there is no real PR interval.
Metabolic
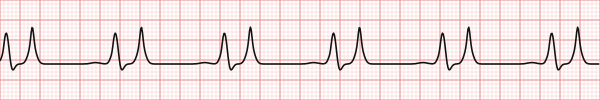
Hyperkalaemia
Tall, narrow, tented T waves and a slowing rate. In a scenario this is a good rhythm to pair with a missed dialysis session or a potassium infusion running too fast.
Pacing
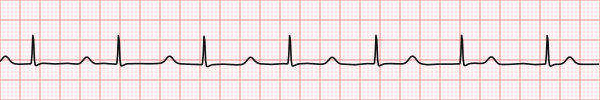
Pacing spikes without capture
The pacemaker fires but nothing follows the spike, while the patient's own P waves carry on underneath. Time to turn the output up, check the pads or call for help.
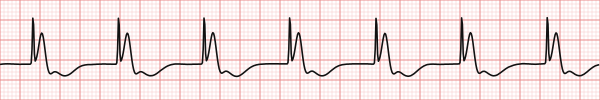
Paced rhythm with capture
Each spike is followed by a broad QRS and a T wave in the opposite direction. Check for a pulse that matches, since electrical capture is not the same as mechanical capture.
Cardiac arrest
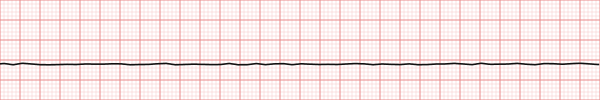
Asystole
A nearly flat line. Before calling it, check the leads, the gain and a second lead. The monitor blanks the pressure, the saturation and EtCO2 along with it.
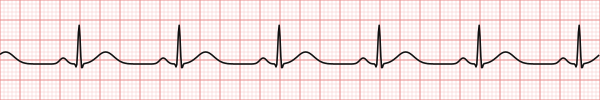
PEA
An organised rhythm with a countable rate, but no pressure and no pleth. The heart rate stays on the screen, which is exactly why PEA catches people out.
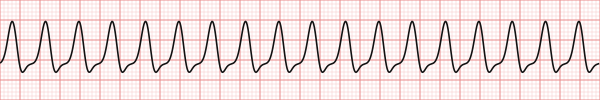
Pulseless VT
The same broad complexes as VT, with no output. Shockable. The only way to tell it from VT with a pulse is the patient, and the arterial line if there is one.
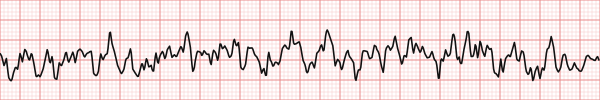
Ventricular fibrillation
Chaotic, irregular waves with no QRS and no rate to count. Shockable. Every channel on the monitor alarms.
Using these rhythms in a scenario
On the controller, tap the rhythm button and pick from the same groups as on this page. The rhythm changes on the monitor straight away, with a heart rate that fits it, so you do not end up with complete heart block at 110. Fine-tune the rate afterwards with the slider and Send to monitor.
Questions
Can I use these rhythm strips in my own teaching?
Yes. Use them in slides, handouts and quizzes. A link back to this page is appreciated, so other educators can find the rest of the library and the live monitor.
Why do the strips look like a monitor lead and not a 12-lead ECG?
Because they come from a patient monitor. A monitor shows a single lead, usually lead II, which is enough to read rhythm and rate but not to localise an infarct. That is also why bundle branch blocks appear as one rhythm here.
What paper speed and scale are the strips printed at?
25 mm/s and 10 mm/mV, the standard settings. One small square is 0.04 seconds and one large square is 0.2 seconds, so a 6-second strip is 30 large squares wide.
How do I show one of these rhythms on a simulated monitor?
Open the app, pair a tablet and a phone, and tap the rhythm button on the phone. The monitor switches immediately and keeps drawing the rhythm live until you change it.